
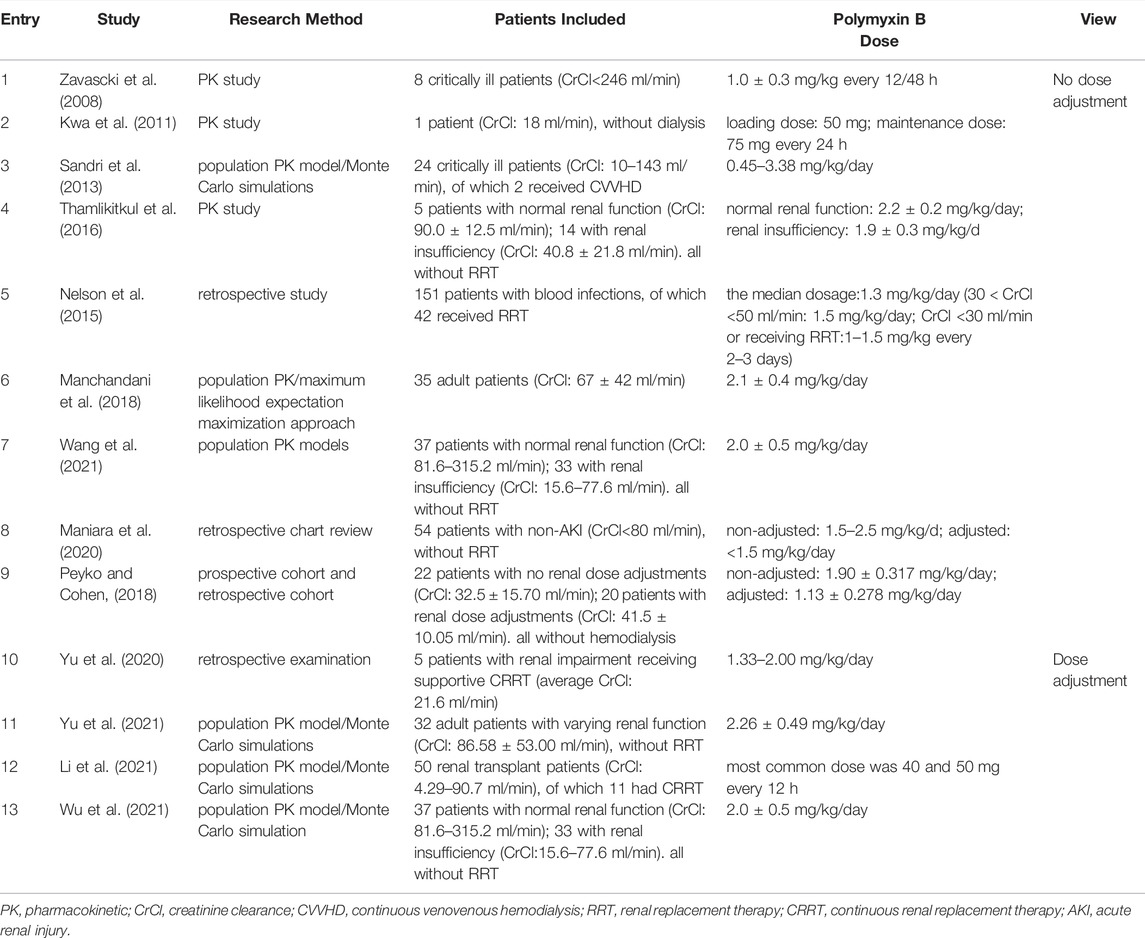
The progression of microbial resistance and consequent failure to eradicate infections, clinically opposes one of the major human strides in medicine, which is the discovery of antimicrobials. The rapidly evolving microbial defense systems are paralleled by relentless efforts of scientists and clinicians to prolong the era of effective antimicrobials. Design of novel molecular entities, rational clinical use, optimization of pharmacokinetic exposure, and adherence to stewardship principles are examples of strategies to halt the development microbial resistance. In this special issue we called upon researcher to publish their endeavors in this arena.The rediscovery of older effective antibiotics has recently gained a momentum probably due to the dwindling number of new antibiotics joining the therapeutic armamentarium and diminishing industry investment. Xuedong Jia et al, 2022 retrospectively studied the salvage treatment of a group of Chinese children infected with carbapenem resistant Gram-negative bacteria with polymyxin B. The antibiotic (mostly used in combination with other regimens) demonstrated efficacy in 52.7% of the cases. However, this efficacy was accompanied with 27.3% acute kidney injury (AKI). The authors also highlighted that appropriate dose and therapy duration may improve outcomes. Furthermore, the loading dose did not improve efficacy avoiding electrolyte imbalances may mitigate toxicity.In a prospective clinical pharmacokinetic study investigating polymyxin B optimal exposure, Zhewei Zu et al, 2022, reported that fAUCss,24h/MIC of ≥22.8 was associated with eradication of blood stream infections caused by carbapenem resistant Klebsiella pneumoniae (CRKP) with MIC£ 1 mcg/mL. A Monte Carlo simulation revealed that a dose of 1.25mg/kg every 12 hours was efficacious against CRKP with such MIC. Polymyxin B -consistent with in vitro studies-demonstrated rapid concentration-dependent bactericidal effect achieving microbiological clearance around day 3 of therapy. The study also emphasized that the pharmacokinetics of the drug in patients with blood stream infections are quite distinctive for these in healthy subjects which could be related to the pathologic changes (Cl; 0.028 ± 0.007 L/kg/h and0.026 ± 0.004 L/kg/h -VD; 0.490 ± 0.142 L/kg and 0.204 ± 0.026 L/kg -T1/2; 12.5 ± 3.11 vs. 5.55 ± 0.942 h, respectively). Finally, the authors attributed the incidence of 55.6% AKI at day 7 of therapy, to the high daily dose and cumulative exposure. Furthermore, they observed a 70% incidence of neurotoxicity and an overlap between exposures responsible for efficacy and emergence of adverse events.A summary of studies discussing the need for dose adjustment in renally impaired patients, Ruifang Nie et al, 2022, argued that polymyxin B is non-renally excreted as evidenced by urine recovery of 0.04-0.86% of the dose in unchanged form. A case report of renally impaired patient showed that the drug had comparable half-life of11.5 h similar to those with normal renal function. In a population PK study, there was a lack of correlation between polymyxin B and creatinine clearance. Additionally, in another PK study, the authors found comparable total polymyxin B exposures in both intact and impaired renal function patients who received administered comparable doses. Furthermore, another two studies illustrated no significant difference in incidence of adverse events, microbiological cure or 30-day mortality. On the other hand, several studies which performed Monte Carlo simulations, demonstrated that creatinine clearance is a significant covariate in polymyxin B clearance, and the dose should be adjusted based on renal function. The authors of this opinion paper conclude that the evidence is insufficient to reach consensus recommendation.Continuing with polymyxins, Xu-ben Yu et al, 2022, studied the pharmacokinetics of polymyxin E (colistin sulfate, administered as active form) in critically ill patients. The authors found that the drug clearance is similar to polymyxin B and dependent on creatinine clearance. Of the patients infected with carbapenem resistant organisms, 60% achieved clinical cure with analogous to polymyxin B. The study showed that colistin sulfate achieved comparable clinical cure rate similar to polymyxin B despite of the use of significantly lower doses which could be attributed to lower pharmacokinetic target based on higher potency and fraction of unbound drug. The above studies provided insights about the clinical use of polymyxins with respect to optimizing dosing and minimizing untoward effects which becomes particularly beneficial when treating carbapenem resistant bacteria in critically ill patients with multi-drug resistant organisms.Tackling another topic, the emergence of multi drug resistant Mycobacterium tuberculosis (MDR-TB), Azimi et al, 2022, conducted a systematic review and meta-analysis of the literature pertaining to the prevalence of TB resistance to linezolid (LNZ). The meta-analysis calculated prevalence (4.2%) of LNZ resistance among all MDR-TB isolate peaking in Spain (22%) and troughing (0.2%) in USA. LNZ resistance to LND develops as a consequence of several genetic mutations leading to changes in the target binding site (23S rRNA). Combination of LNZ with other anti-tubercular medications can produce synergism, shorten treatment duration, and obliterate latent infections.Since irrational prolonged antibiotic administration could promote the emergence of resistance, He et all, 2022, investigated the risk factors associated with prolonged antibiotic use in pediatrics with bacterial meningitis. The study revealed that even with use of guidelines recommended regimens, the augmented renal clearance (ARC) was an independent risk factor for prolonged antibiotic use. The author observed higher incidence of longer hospital stay, antibiotic regimen adjustments, and neurologic complications in ARC group, which was explained by in ability of renally excreted antibiotics to attain pharmacokinetic/pharmacodynamic targets.The research on microbial resistance constitutes an integral part of our efforts to ameliorate patient care. As microbial pathogens continue to evolve and exhaust the available treatment options, the discovery of novel antibiotics, further understanding of resistance patterns and methods to overcome them should remain a priority for the scientific community. This endeavor should be a combined effort of governmental/non-governmental organizations, academic institutions and pharmaceutical industry enterprises to secure adequate funding and maximize the outcomes.
Editorial16 March 2023
Editorial: Advances in antimicrobial therapy and combating resistance

Introduction: Tuberculosis (TB), resulting from infection by Mycobacterium tuberculosis (M. tuberculosis), is an important and resurgent global health problem. Linezolid is an effective antibiotic with which to treat patients failing drug-resistant TB treatment. In this study, we performed a systematic review and meta-analysis to investigate the prevalence of linezolid resistance among MDR-TB isolates, global.
Method: Using the PRISMA guidelines, databases of, Embase, and PubMed and Web of Science were searched systematically from Janurary 2000 to April 2021. Statistical analyses were performed by using Comprehensive Meta-Analysis software. Heterogeneity reported by using the t2 and Q statistics. Egger’s weighted regression and Begg’s rank correlation in combination with funnel plot were used to evaluate any possible publication bias.
Results: A total of 25 studies were included from 14 different countries, with the majority of the China (n=5), Turkey (n=4). Also, 7366 patients infected with MDR M. tuberculosis were enrolled in current study. Of the study population, 97 patients were co-infected with HIV and 18 patients with HCV. Furthermore, 28 patients had diabetes and139 patients were alcohol abuser. Overall, 4956 MDR M. tuberculosis strains were isolated from TB patients. The pooled frequency of linezolid resistance among clinical isolates of MDR M. tuberculosis was 4.2% (95%). Begg’s (p = 0.72) / Egger’s (p = 0.03) test, showed that there was some evidence of publication bias.
Conclusion: Our study showed that the global linezolid resistance among MDR-TB is low and this antibiotic can be used as an anti-tuberculosis drug in treatment regimes.

ORIGINAL RESEARCH
16 June 2022
Xu-ben Yu, 11 more and Jing-Ye Pan
13 Authors
- XY
Xu-ben Yu
Department of Pharmacy, China
- XZ
Xiao-Shan Zhang
Department of Pharmacy, China
- YW
Ye-Xuan Wang
Department of Pharmacy, China
- YW
Yu-Zhen Wang
Department of Pharmacy, China
- HZ
Hong-Min Zhou
Intensive Care Unit, China
- FX
Fang-Min Xu
School of Pharmacy, China
- JY
Jun-Hui Yu
School of Pharmacy, China
- LZ
Li-Wen Zhang
School of Pharmacy, China
- YD
Ying Dai
Department of Pharmacy, China
- ZZ
Zi-Ye Zhou
Clinical Research Center, China
- CZ
Chun-Hong Zhang
Department of Pharmacy, China
- GL
Guan-Yang Lin
Department of Pharmacy, China
- JP
Jing-Ye Pan
Intensive Care Unit, China
Background
Presently, colistin is commercially available in two different forms, namely colistin sulfate and its sulphomethylated derivative, colistimethate sodium (CMS). However, in the currently reported studies, most of the clinical studies on colistin for parenteral use is refer to CMS. Data on the pharmacokinetics (PK), clinical efficacy, and side effects of colistin sulfate in clinical use have not been reported.
Methods
This retrospective study was performed in carbapenem-resistant organisms (CRO)- infected patients treated with colistin sulfate for more than 72 hours. The population pharmacokinetic model was developed using the NONMEM program. The clinical outcomes including clinical treatment efficacy, microbiological efficacy, and nephrotoxicity were assessed. Monte Carlo simulation was utilized to calculate the probability of target attainment (PTA) in patients with normal or decreased renal function.
Results
A total of 42 patients were enrolled. 25 (59.52%) patients were considered clinical treatment success, 29 (69.06%) patients had successful bacteria elimination at the end of treatment. Remarkably, no patient developed colistin sulfate-related nephrotoxicity. A total of 112 colistin concentrations with a range of 0.28 to 6.20 mg/L were included for PK modeling. The PK characteristic of colistin was well illustrated by a 1-compartment model with linear elimination, and creatinine clearance (CrCL) was identified as a covariate on the clearance of colistin sulfate that significantly explained inter-individual variability. Monte Carlo simulations showed that the recommended dose regimens by the label sheet of colistin sulfate that daily dose of 1 – 1.5 million IU/day, given in 2-3 doses could attain PTA > 90% for MICs ≤ 0.5 μg/mL, but it was risking of subtherapeutic exposure for MIC ≥ 1 μg/mL in renal healthy patients at the daily dose of 1 million IU/day.
Conclusion
Renal function significantly affects the clearance of colistin sulfate. A dose of 750,000 U every 12 h was recommended for pathogens with MIC≤ 1 μg/mL. The dosage recommended by the label inserts had a risk of subtherapeutic exposure for pathogens with MIC≥2 μg/mL. Despite patients with acute renal insufficiency have higher exposure, dose reduction was not recommended.